The First Sample: Consent, Custody, and the Residual Bloodspots of Newborn Screening
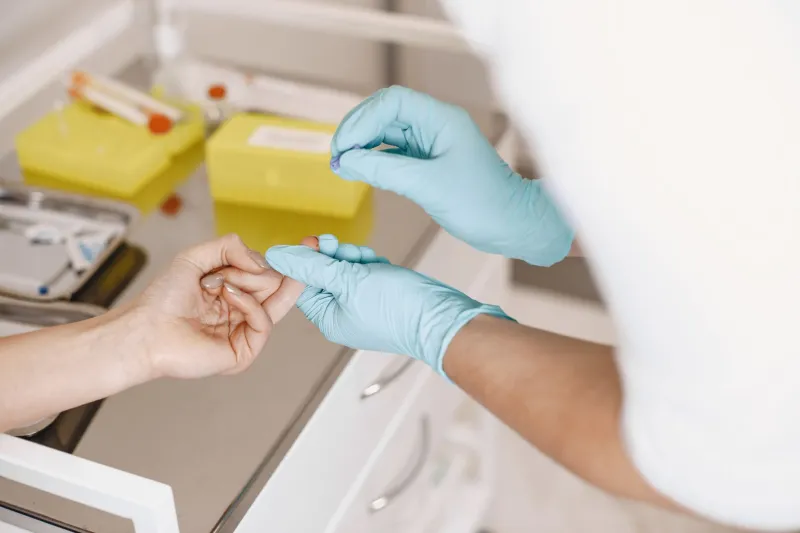
Newborn screening is often described as a public health success story, and for good reason: a heel prick administered in the first days of life can identify rare but treatable conditions before symptoms appear. But the story does not end when the screening result is reported. In many states, the same dried blood spot card that made the test possible is retained for years, sometimes decades, and may become a resource for research, quality assurance, method development, or—under some circumstances—outside requests. That afterlife is where the governance questions begin.
A Universal Test With a Long Afterlife
Every state operates a newborn screening program, and most require screening unless a parent objects on religious or other grounds. The specimen itself is typically collected on a filter-paper card, dried, and sent to a state laboratory. After testing, residual spots may be stored. The length and terms of storage vary widely. Some states retain spots for a few months; others keep them for many years. Some permit research use only with parental consent, some allow deidentified research under an opt-out model, and some impose tighter restrictions or prohibit research use altogether.
For families, this is an unusual kind of data encounter. It is nearly universal, occurs at a moment of exhaustion and adjustment, and is often explained through a brochure or a brief conversation in a hospital room. The screening test itself is usually framed as routine and medically beneficial. The retention of residual specimens is a separate policy question, but it is frequently folded into the same paperwork—or left unmentioned.
The State-by-State Patchwork
The result is a governance landscape built from fifty different statutes, regulations, and laboratory policies. Variations appear along several dimensions: how long spots are kept, who may access them, whether parents can opt out of storage or research, whether specimens may be used for commercial product development, and what notice is given at the point of collection.
Some states treat residual spots as part of the medical record or as public health property. Others recognize them as biological specimens subject to specific consent rules. A few require parents to be informed that spots may be retained and give them a clear opportunity to decline. In practice, the difference between an opt-out state and a consent state can be substantial: one family may never learn that storage is occurring, while another may be asked to make a documented choice.
What Parents Are Told—and When
The timing of disclosure matters. Newborn screening is often presented prenatally or immediately after birth, when parents are managing recovery, feeding, and sleep deprivation. Even well-designed materials must compete with a flood of information. When retention and research use are buried in a packet, the resulting consent—if it can be called that—is thin.
A more legible approach would separate two decisions that are often conflated: whether to screen the infant, and whether to retain the residual specimen for future uses. Screening itself has a strong public health rationale and an established clinical benefit. Storage for research is a different proposition, with different risks and different public benefits. Parents can reasonably be asked to consider them separately, in plain language, with enough time to understand what is being proposed.
Research Value and Governance Risk
Residual spots have real scientific value. They can support quality improvement, assay validation, rare disease research, and public health surveillance. At a time when genomic data is increasingly valuable, however, the specimens also raise familiar concerns. Dried blood spots contain DNA. Even when direct identifiers are removed, genomic data can be difficult to anonymize in any absolute sense. Reidentification risks may be low in many contexts, but they are not zero, and they grow as data linkages become more sophisticated.
Federal law does not provide a comprehensive framework for this specific category of specimens. The Common Rule governs much human-subjects research, but its application depends on funding source, institutional policy, and whether the specimens are identifiable. HIPAA may apply to covered entities, but state laboratories and public health programs do not always fit neatly into its categories. The result is a reliance on state law and institutional practice—an arrangement that can produce sensible local rules but makes national consistency difficult.
Law Enforcement and the Custody Question
Another unresolved issue is access by law enforcement. State policies differ on whether residual spots may be released in response to a subpoena, warrant, or other legal request. Some states explicitly restrict such access; others are silent, leaving the answer to laboratory policy or case-by-case legal review. For the public, the question is not whether newborn screening is a tool for police investigation—it is not designed to be—but whether stored specimens can be repurposed in ways families never anticipated.
A clear custody framework would help. It would specify who controls the specimens, what purposes are authorized, how requests from outside government are handled, and what notice, if any, parents receive. Transparency about these rules is itself a form of accountability.
Principles for a More Legible Regime
A more coherent approach need not be uniform in every detail. It could, however, rest on a few shared principles: separate screening from storage; give parents clear, timely, and plain-language information; provide a genuine opportunity to decline nonessential uses; limit retention to what is justified; publish access and research policies; and establish independent oversight for requests that fall outside routine public health use.
Newborn screening earns its public trust by delivering clear clinical benefits. The governance of residual blood spots should protect that trust rather than trade on it. The first sample a person gives is also one they cannot remember giving. That makes the obligation to explain—and to limit—its later uses especially strong.